

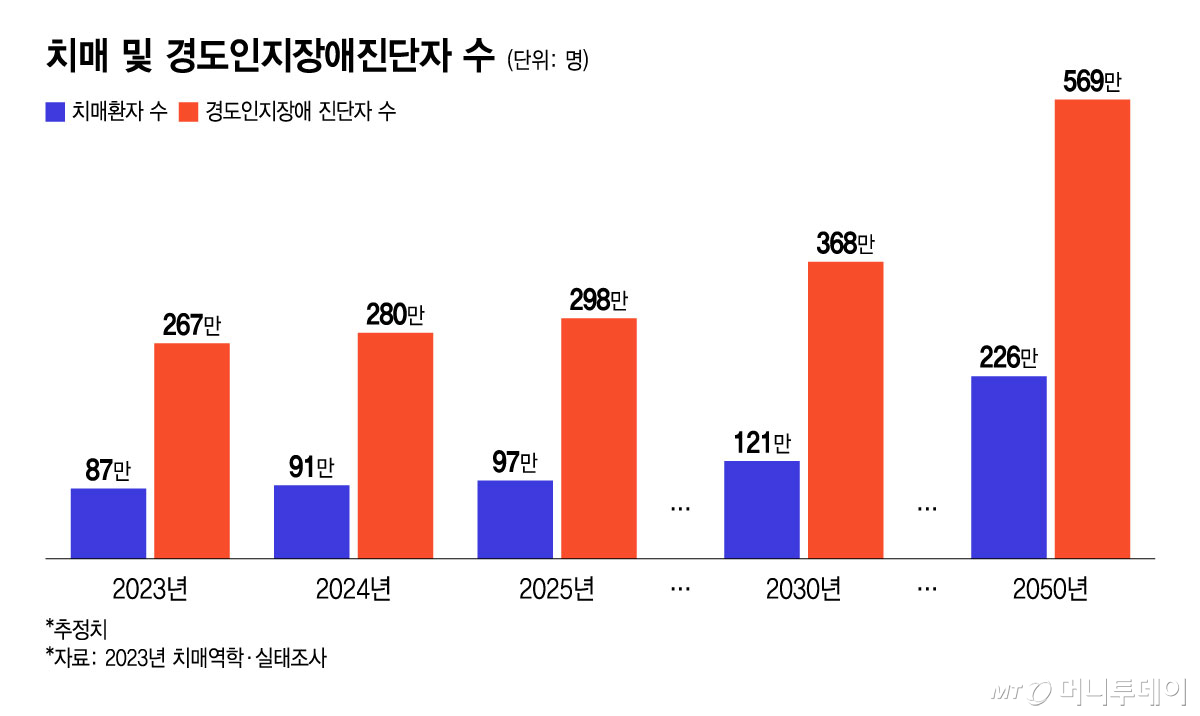
Recently, as actor Jeon Won-ju disclosed his diagnosis of mild cognitive impairment (MCI), interest in MCI has increased. However, one should not judge an individual's condition or future course based solely on a few scenes seen on broadcast. MCI is a state where cognitive functions such as memory, language, attention, and judgment have declined compared to before, but the ability to perform independent daily activities, such as taking medication, managing finances, and using public transportation, is generally maintained. It is distinguished from dementia, in which independence in daily life has clearly collapsed.
The term "pre-dementia stage" is only half correct
MCI is often called the "pre-dementia stage," but not everyone progresses to dementia. It is a clinical syndrome that manifests due to various causes, rather than a single disease. Alzheimer's disease is a common cause, but cerebrovascular disease, Lewy body disease, depression, sleep disorders, drug side effects, thyroid disease, vitamin B12 deficiency, and hearing or vision loss can also be causes or aggravating factors. Therefore, diagnosis is made by comprehensively considering medical history, daily functioning, standardized cognitive tests, blood tests, and brain MRI. There is no common medication used for all patients. Treatment is divided into correcting the cause, managing risk factors, and selective disease-modifying treatment for confirmed Alzheimer's disease. When considering this treatment, it is necessary to confirm the underlying pathology through amyloid positron emission tomography (PET) or cerebrospinal fluid tests.
10.9% of MCI patients progress to dementia annually on average
A study analyzing data from 33,115 MCI patients across 89 studies published in 2025 found that over an average of 5.2 years, 41.5% of patients receiving specialized care and 27% of community-based subjects progressed to dementia. The annual conversion rates were 10.9% and 5.9%, respectively. Typically, because patients with distinct symptoms or high risk visit specialized care settings, the conversion rate is reported higher there. On the other hand, in both environments, about half maintained their cognitive state during the follow-up period, and some recovered to normal range.
Individual risk varies depending on Alzheimer's disease pathology, the degree and progression speed of memory impairment, brain atrophy and vascular damage, age, and genetic factors. Therefore, rather than determining prognosis based solely on the diagnosis, it is necessary to identify the cause and track changes.
Aerobic exercise significantly improves cognitive function
In a study analyzing 33 randomized trials involving 1,996 people, aerobic exercise relatively clearly improved overall cognitive function in MCI patients and had a smaller but significant effect on memory. Computerized cognitive training, analyzed across 18 studies involving 1,059 people, also moderately improved cognitive test scores.
In the US POINTER study in the United States, 2,111 people aged 60 to 79 at risk of cognitive decline were observed for two years. The group that received systematic expert support for exercise, healthy diet, cognitive and social activities, and blood pressure and blood sugar management showed a greater improvement in cognitive function than the group that only received lifestyle guidelines. This demonstrates that managing multiple lifestyle factors together can produce measurable changes within two years.
In actual management, it is recommended to aim for about 150 minutes of moderate aerobic exercise per week and strength training twice a week, tailored to health status, and to gradually increase the difficulty of cognitive training while evenly addressing memory, attention, and executive function. A diet centered on vegetables, whole grains, legumes, fish, and nuts, smoking cessation, moderation in alcohol consumption, sufficient sleep, correction of hearing and vision, treatment of depression and sleep apnea, and social interaction are also important. Hypertension, diabetes, and hyperlipidemia must also be managed consistently. In 2024, the Lancet Dementia Commission estimated that 14 modifiable factors could be associated with approximately 45% of all dementia cases. This does not mean that an individual's risk is reduced by exactly 45%, but rather that the proportion of preventable factors is significant.

Why must amyloid be removed "early"?
In Alzheimer's disease, amyloid-beta protein continuously forms clumps (plaques) for about 20 years before symptoms appear, followed by the spread of tau proteins and damage to nerve cells. Since it is difficult to revive already lost nerve cells, the goal of treatment is not to restore memory to its original state, but to slow down the rate of cognitive and functional decline.
In an 18-month trial involving MCI or mild Alzheimer's disease dementia patients confirmed to have positive amyloid, lecanemab slowed the rate of deterioration in cognitive function and daily living activities by about 27% and significantly reduced amyloid accumulated in the brain. In a 36-month follow-up, the group that started treatment from the beginning had a risk of worsening to the next stage that was about 30% lower than the group that started after 18 months. In the three-year follow-up of donanemab as well, the progression risk in the early treatment group was 27% lower, and more than three out of four patients evaluated about 18 months after treatment reached the amyloid removal target.
These results show that removing amyloid is important in the early stages when nerve cell damage is less. However, this does not apply to all MCI patients. It is necessary to first confirm Alzheimer's disease pathology, and MRI examinations before and after treatment as well as evaluation by a specialist are required due to the risk of brain edema or microbleeds.
Alzheimer's disease pathology alone cannot explain all cognitive decline... Depression and other factors also have an impact
In a study analyzing 248 elderly people with positive amyloid in 2022, tau was most closely associated with cognitive function decline. Tau levels alone could explain about half of the differences in cognitive function among participants, at 46-47%. Amyloid accounted for about 16%, and brain atrophy for about 25-29%. In changes over time, the pathway where amyloid accumulates, tau spreads, and this leads to brain atrophy explained about half of the differences in cognitive decline.
This does not mean that the remaining half is entirely due to lifestyle habits. Cerebrovascular damage, other brain diseases, synaptic health, cognitive reserve formed by education and intellectual activities, depression, sleep disorders, hearing or vision loss, systemic diseases, and medications all contribute together. Even with the same amount of amyloid and tau, the timing and speed of symptoms can vary depending on these conditions. Therefore, anti-amyloid treatment and lifestyle management should be done together. Medication reduces amyloid, while managing blood pressure, blood sugar, cholesterol, depression, sleep, exercise, cognitive training, smoking, alcohol consumption, and social isolation helps maintain the resilience of cerebral vessels and the brain.
If family members notice repeated questions during holidays, confusion on familiar routes, mistakes in managing medication or money, or distinct lethargy or personality changes, it is advisable to record these cases and get evaluated at a specialized institution. MCI is not a confirmed state of dementia, but an important period to find the cause and intervene in modifiable risk factors.
Help = Kang Dong-woo, Department of Psychiatry, St. Mary's Hospital, The Catholic University of Korea Seoul


 in THEBIO


